

The pressing problem in the lab
Too many drug candidates mek it past cell work but flop in clinic, an’ di root too often sit in di animal model. Researchers deh use models dat lack humanized GIPR and GLP‑1R signalling, an’ di metabolic response nuh match patient biology. This problem stretch beyond diabetes into inflammation research—see how autoimmune pathways fold in when metabolic stress change immune tone via autoimmune disease models. WHO estimates over 422 million adults live with diabetes, so wrong preclinical hits mean real-world harm and big sunk cost for development teams.
Why humanized GIPR and GLP‑1R shift outcomes
GIPR and GLP‑1R agonists act on glucose homeostasis, appetite, and downstream cytokine responses. A humanized model reflect di receptor pharmacology and receptor–ligand kinetics closer to patient tissue. When receptors differ between species, dose–response and receptor desensitization diverge, and dat lead drug teams to misread efficacy or toxicity. A humanized model help bridge dat gap, improve target engagement readouts, and reduce false positives in preclinical studies.
Design principles for robust in vivo metabolic disease models
Buildin’ a useful model need clear endpoints and matched biology. Keep these elements tight:
– Humanized receptor expression (GIPR, GLP‑1R) in relevant tissues (pancreas, CNS, adipose).
– Metabolic phenotyping: glucose tolerance, insulin secretion dynamics, energy balance metrics.
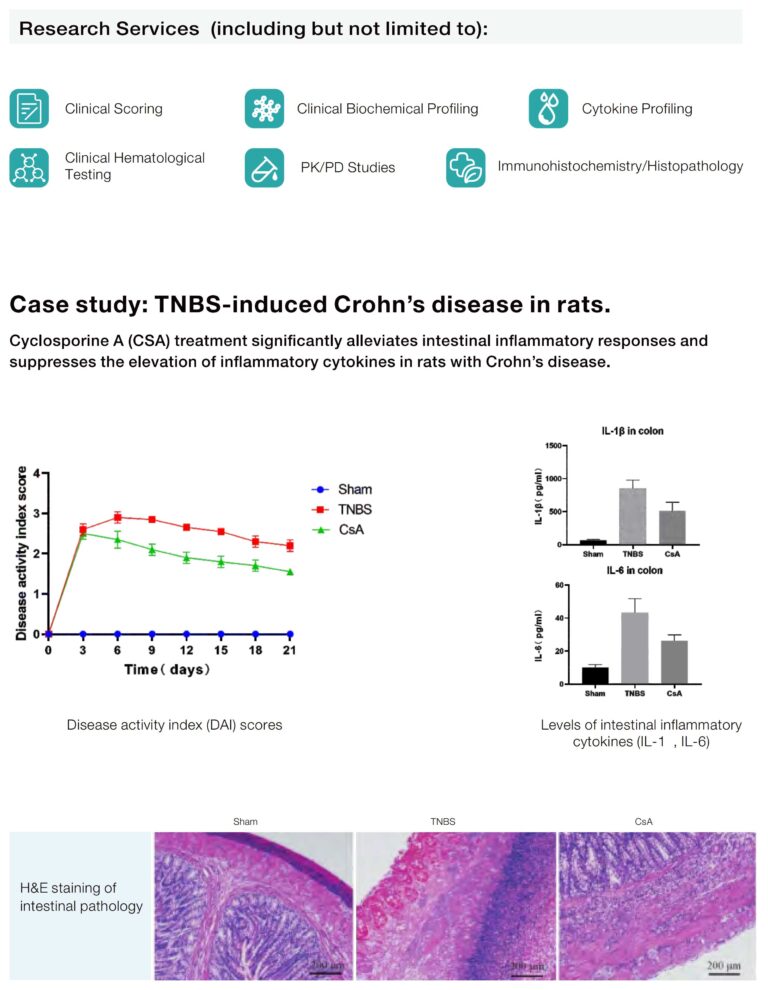
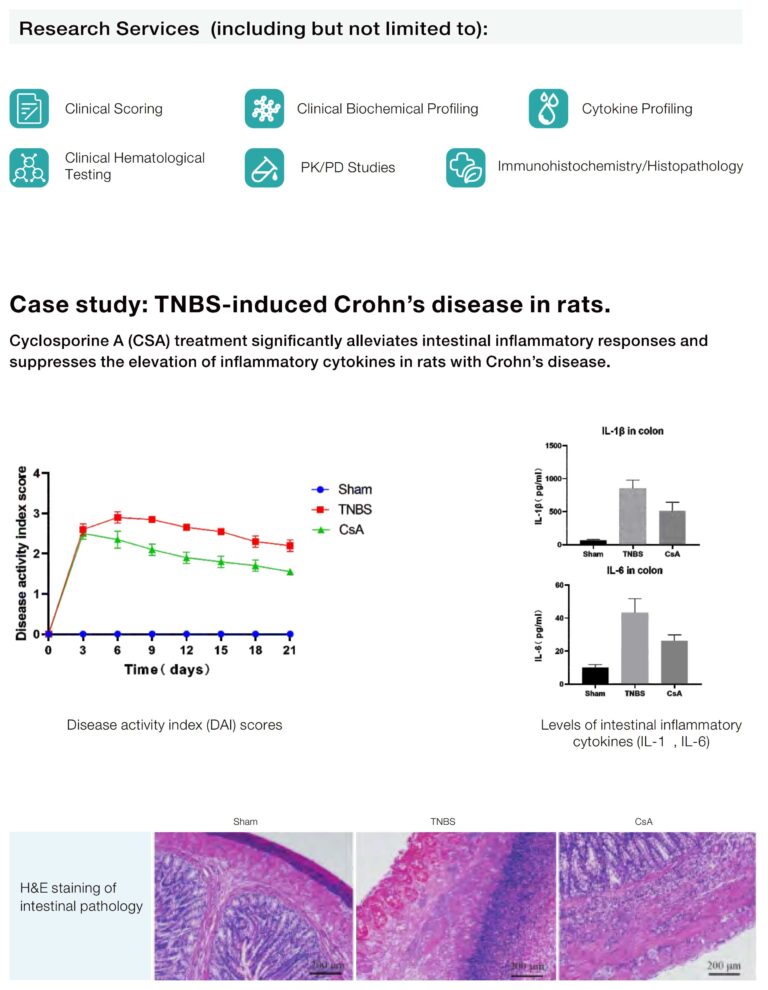
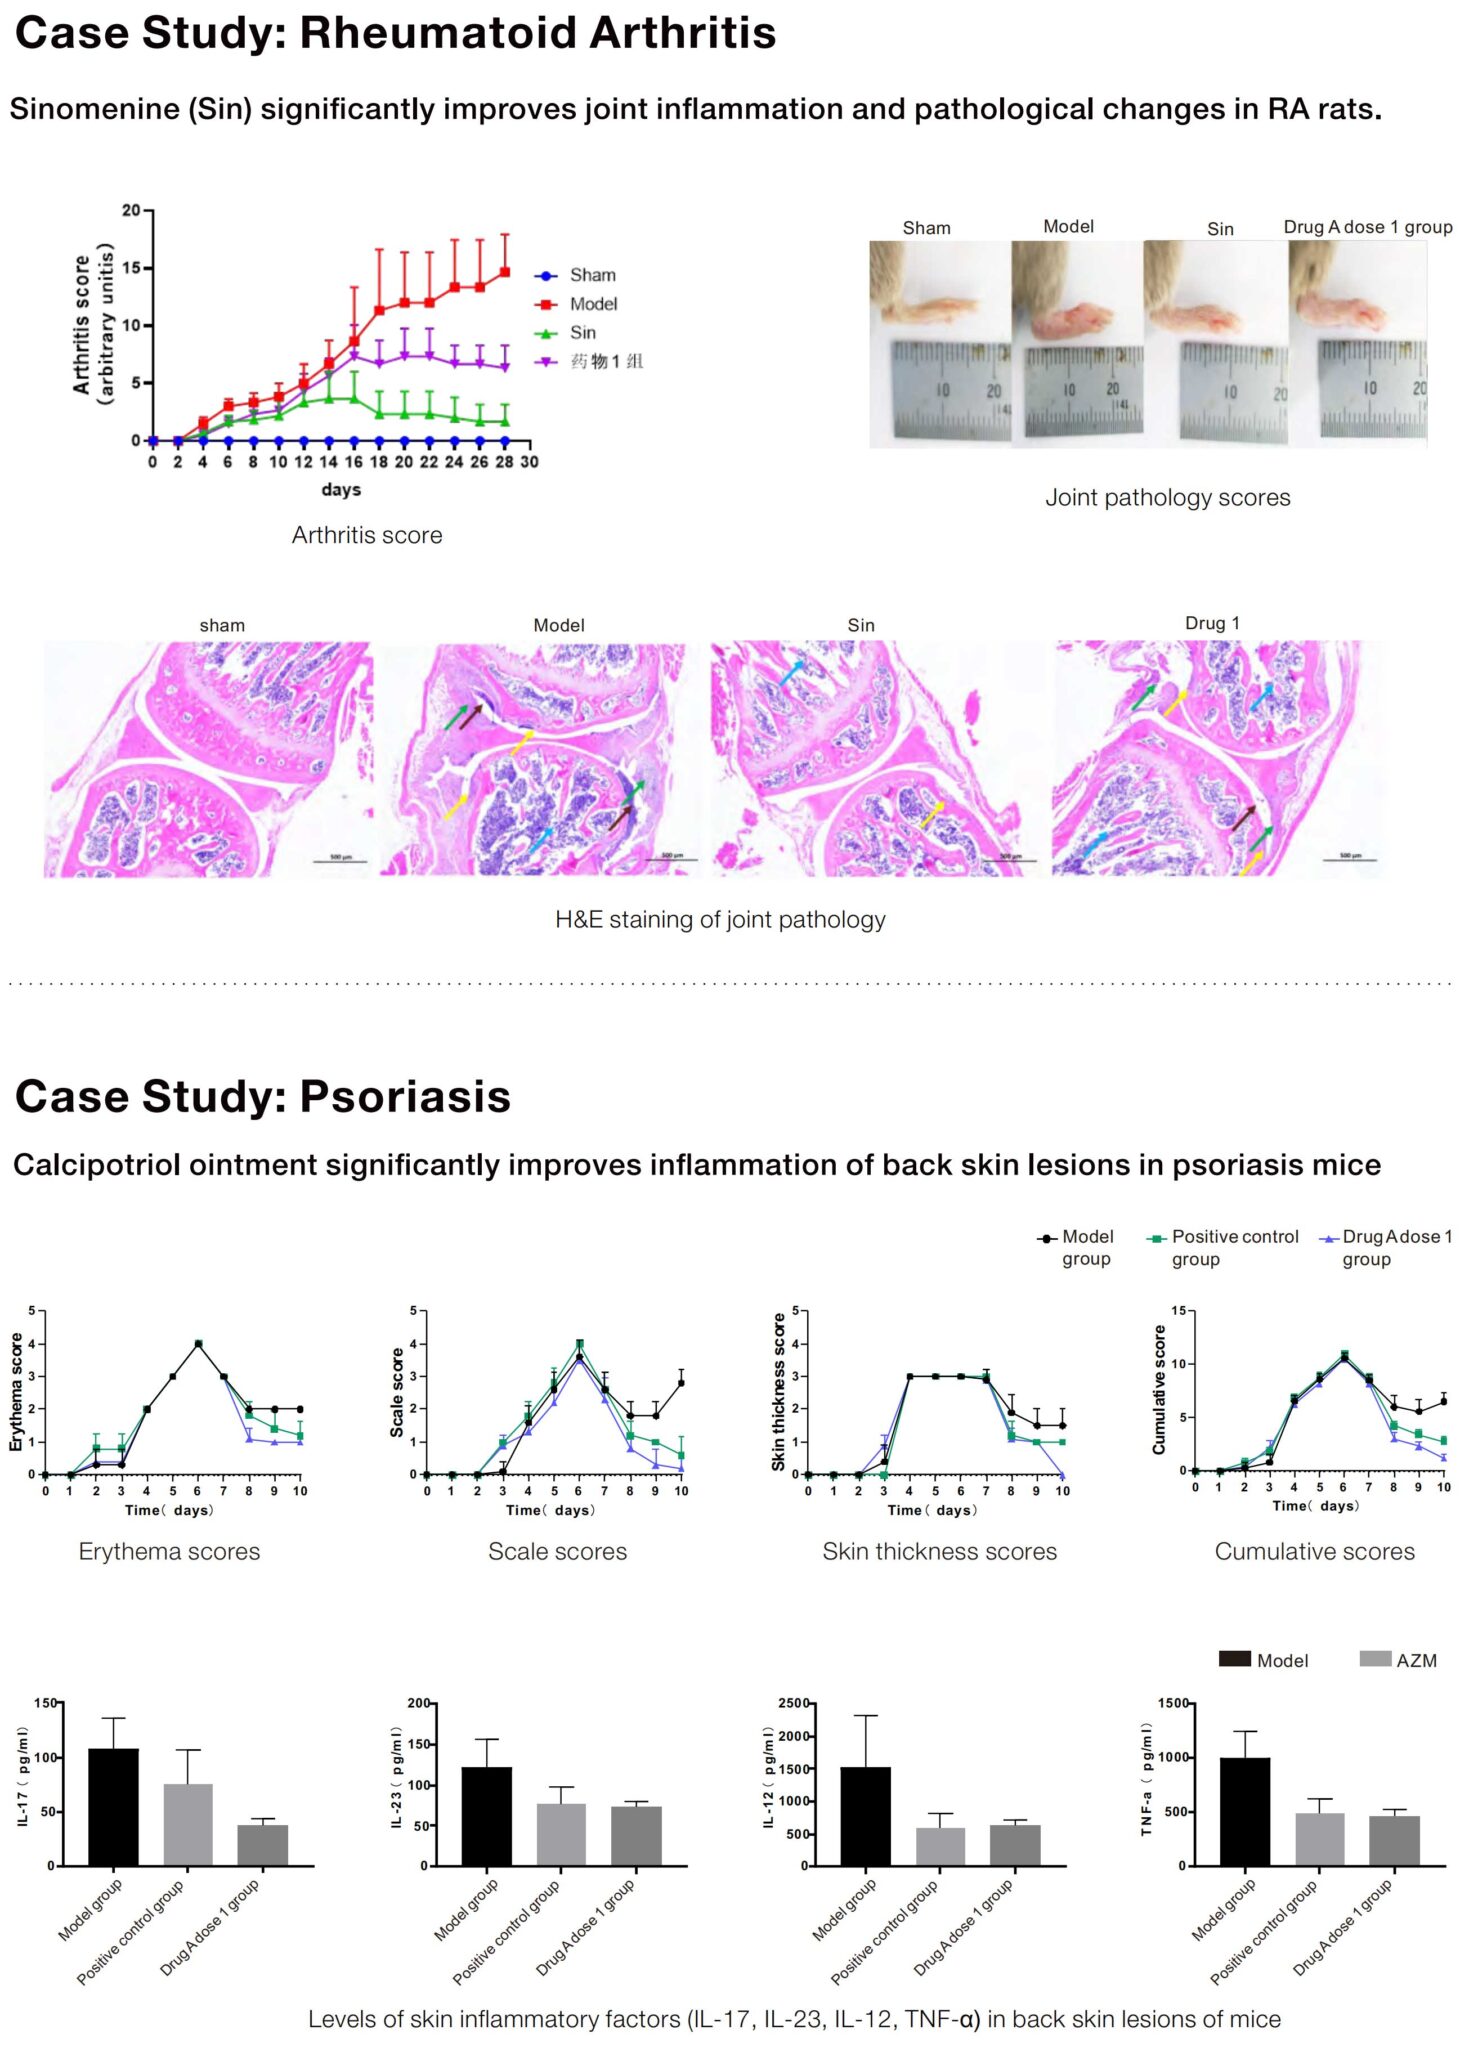
– Immune profiling layers where metabolic and inflammatory axes intersect (basic cytokine panels, immunophenotyping).
Pair experimental models of autoimmune disease—like T cell transfer or antigen-induced models—with metabolic readouts to capture cross-talk. These combined datasets help predict human response much better than any single-axis model.
Operational teardown: what teams routinely miss
Too many groups skip rigorous validation steps. A proper operational production teardown must document receptor expression levels, ligand-binding affinities, and pharmacokinetics — and yes, embed {main_keyword} and {variation_keyword} into that workflow so handover remains explicit. Validate with orthogonal assays: receptor autoradiography, RNA expression panels, and functional insulin/glucose flux studies. Without these, you build on shaky assumptions and waste resources downstream.
Common alternatives, and why they fall short
In vitro systems and non‑human primates each bring value but no single alternative replaces humanized in vivo models. Cell systems show pathway mechanisms but miss systemic interplays. Primate work is costly, slow, and still not an exact human match for receptor regulation. Humanized rodent models offer a balance—scalable, modulable, and amenable to immune co‑modelling—so long as teams validate receptor pharmacology early.
Practical missteps to avoid
Don’t rely on a single biomarker or a single time point. Don’t assume receptor expression equals physiological coupling. Don’t ignore immune context—metabolic drugs often alter cytokine milieu, so simple glucose endpoints only tell part of di story. —And remember, reproducibility need standard operating windows for glucose tolerance tests and pharmacokinetic sampling.
Real-world anchor and precedent
Clinical trial failures tied to poor preclinical translation have shaped regulators’ guidance and sponsor behavior over the last decade, an’ dat history push teams to demand models that better mirror human receptor pharmacology. Lab groups at major centers, including university research hubs, now routinely compare humanized receptor readouts against known clinical pharmacodynamics to validate model fidelity.
Three golden rules for selection and evaluation
1) Receptor fidelity: confirm human‑level GIPR/GLP‑1R expression and ligand potency through binding and functional assays. 2) Multiplexed endpoints: combine metabolic, immune, and PK/PD measures so a single mismatch flags model limits. 3) Reproducible validation: publish SOPs for glucose tolerance windows, sampling intervals, and cytokine panels so others can replicate. These metrics cut down on guesswork and give teams measurable gates for go/no‑go decisions.
Use models that pass those gates and yuh save time, money, an’ heartbreak—an’ dat’s where Jennio Biotech fit natural into di workflow, providin’ validated humanized models and integrated datasets that map straight back to clinical endpoints. —Trust built on proof, not press releases.